The albumin correction factor for anion gap acts as an approach to modify the anion gap when albumin is decreased. Because albumin is a major unmeasured anion in the blood, hypoalbuminemia can make the gap look reduced than it really is. An easy-to-use Anion Gap Calculator can perform this adjustment so the result more accurately reflects the patient’s true acid-base disorders status.
The standard correction is 2.5 mEq/L per 1 g/dL albumin below the usual serum albumin reference range. To put it another way, if albumin is reduced, the corrected anion gap increases to offset the missing negative charge from albumin and support laboratory interpretation.
What Is the Anion Gap?
The anion gap is a computed value that assists clinicians in interpreting serum electrolytes and evaluate for acid-base problems. It is typically based on serum sodium, serum chloride, and serum bicarbonate. The classic formula is:
Anion gap = sodium − (chloride + bicarbonate)
This value represents the discrepancy between routinely measured positively charged ions and negatively charged ions in the blood. In blood chemistry, a normal gap implies balanced unmeasured ions, while an abnormal gap can signal a metabolic derangement. The anion gap is most often used in acid-base evaluation to help identify metabolic acidosis, especially when the cause is not obvious from the initial lab results.
Understanding the gap requires more than memorizing a formula. It also helps to know that the gap is influenced by unmeasured ions, especially protein anions such as albumin. That is why the measured value can shift even when the clinical situation has not changed for the better or deteriorated.

How Albumin Changes the Anion Gap
Albumin is the most important negatively charged protein in plasma. As it supplies many protein anions, it has a major effect on electrolyte balance and the measured anion gap. When albumin drops, the body loses some of those unmeasured negative charges, so the anion gap may decline as well.
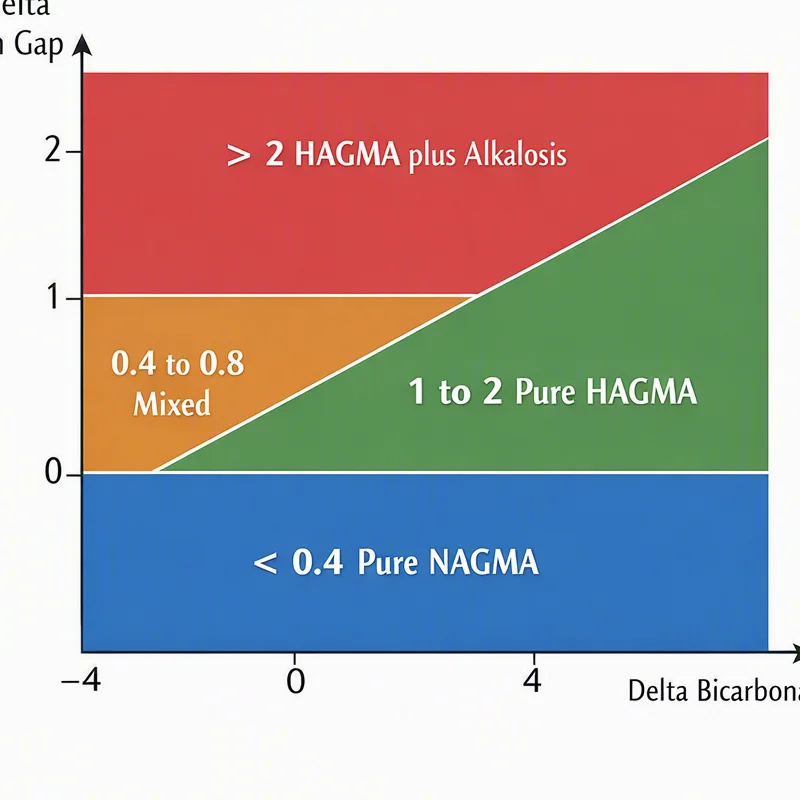
This explains why hypoalbuminemia can mask an underlying acid-base problem. A patient may seem to have a normal gap even when there is actually a high-gap disorder present. That can lead to missed hidden acidosis unless the albumin level is considered.
Albumin matters because acid-base chemistry is about electrical neutrality. If fewer albumin molecules are present, fewer negative charges are present. The result is a decreased measured gap, even though the true acid-base balance may be abnormal. This is one of the key reasons to incorporate albumin into diagnostic interpretation.
What Is the albumin correction factor?
The albumin adjustment factor is the amount added to the measured anion gap to account for low albumin concentration in serum. The common adjustment formula uses 2.5 mEq/L for every 1 g/dL decrease in serum albumin below the standard reference level, often taken as 4.0 g/dL.
In practice, the formula is often written as:
Corrected anion gap = measured anion gap + 2.5 × (4.0 − serum albumin)
This adjustment estimates what the gap would look like if albumin had been normal. It transforms a measured value into a more clinically meaningful corrected value. For many clinicians, this improves practical usefulness when evaluating metabolic acidosis and deciding whether further workup is needed.
The key point is that the correction is an approximation, not a perfect truth. Still, it is widely used because it improves lab result interpretation, especially when the albumin level is clearly below the usual normal range.
How to Adjust the Anion Gap for Albumin
Adjusting the anion gap is simple once you know the measured anion gap and the serum albumin level. The process is simple to apply in a calculator or by hand.
Steps for calculation:
- Find the measured anion gap from sodium, chloride, and bicarbonate. Review the serum albumin value and make sure the units are in g/dL. Take away the albumin from 4.0 g/dL, if 4.0 is the reference point being used. Apply that difference by 2.5 mEq/L per 1 g/dL albumin. Combine the result to the measured anion gap.
Calculation example:
When the measured anion gap is 10 mmol/L and serum albumin is 2.0 g/dL:
Correction = 2.5 × (4.0 − 2.0) = 5.0 mEq/L
Corrected anion gap = 10 + 5 = 15 mmol/L
This demonstrates why converting units matters. Although the correction is often written as mEq/L, the anion gap is commonly reported in mmol/L, and many labs use the terms interchangeably in this context. The key step is to keep units consistent and understand how the calculator handles them.
A good Anion Gap Calculator automates this process and reduces calculation errors. It can also support more efficient medical calculator use at the point of care, where quick clinical interpretation is often needed.
When to Consider an Anion Gap Calculator
An Anion Gap Calculator is most useful when you are reviewing lab values in a patient with low albumin or uncertain acid-base changes. It links routine chemistry results with a clearer acid-base picture.
A calculator is useful when:
- Albumin is below normal and you want an albumin-adjusted anion gap. You suspect metabolic acidosis but the gap appears normal. The clinical picture suggests acid-base evaluation is incomplete without correction. You want a quick diagnostic interpretation at the bedside or during chart review.
The calculator is particularly valuable in inpatients, severely ill patients, and anyone with altered protein levels. In these settings, the measured value may not reflect the true corrected value. By adjusting for albumin, the calculator improves clinical utility and can uncover a metabolic problem that would otherwise be overlooked.
Common Causes of a High or Normal Anion Gap
When evaluating metabolic acidosis, the anion gap helps differentiate between high anion gap metabolic acidosis and normal anion gap metabolic acidosis. A corrected result can shift your assessment from one group to another.

Typical causes of high anion gap metabolic acidosis include:
- Lactate acidosis Acidosis from ketones Renal impairment Other forms of acid retention or toxin exposure
In lactic acidosis, elevated lactate adds unmeasured anions to the blood. In ketoacidosis, ketone bodies raise the gap. In renal failure, stored acids collect and raise the anion gap.
A normal result does not always dismiss a high-gap process if albumin is low. That is where the albumin correction factor becomes important in practice. By adjusting for hypoalbuminemia, you may detect a true high-gap state that was hidden by a apparently normal result.
Frequent Errors in Protein Correction
A number of errors can reduce the usefulness of albumin correction in everyday clinical interpretation. Many of these are basic, but they can lead to major analysis errors.
Frequent pitfalls include:
- Applying the wrong measurements for albumin or the anion gap Using the wrong comparison range for serum albumin Overlooking that the correction is only an estimate Ignoring other electrolyte abnormalities Using the corrected anion gap without considering the full clinical picture
A further common issue is overlooking related chemistry results such as calcium ion levels. Although ionized calcium is not part of the formula, it can matter in the broader evaluation of acid-base and electrolyte disorders. The same is true for other markers that affect interpretation of the patient’s condition.
Keep in mind that a corrected anion gap should not replace clinical judgment. It is a tool that improves test interpretation, not a standalone diagnosis. Consistently consider the full pattern of electrolyte levels, symptoms, and context.
FAQ About Albumin Correction and Anion Gap
Does low albumin always mean the anion gap is falsely low?
No. Low albumin often lowers the anion gap, but not every low value is misleading. The effect depends on the degree of albumin reduction, the overall interpretation of the anion gap, and the rest of the lab pattern. Low albumin can create apparently normal results or make a truly abnormal gap appear less impressive, which is why correction is helpful.
What correction factor is most commonly used?
The most common correction uses 2.5 mEq/L for every 1 g/dL drop in blood albumin below about 4.0 g/dL. This produces an albumin-adjusted anion gap that better reflects the patient’s acid-base status.
Can the corrected anion gap change diagnosis?
Yes. In some patients, correction can reveal metabolic acidosis that was hidden by low albumin. This may expose occult acidosis and affect clinical decision-making, especially when deciding whether to investigate causes such as lactic acidosis, ketoacidosis, or renal failure.
What is the albumin correction factor for anion gap?
The albumin adjustment factor is typically 2.5 mEq/L per 1 g/dL albumin below the normal reference point. It gets added to the measured anion gap to calculate a more accurate corrected anion gap when albumin is low.
Why does low albumin reduce the anion gap?
This protein holds a negative charge as a leading protein anions in blood plasma. With lower albumin levels, the blood has less unmeasured negative ions, so the anion gap reading lowers. This can distort acid-base evaluation unless a correction factor is made.
How do you determine the adjusted anion gap?
Take the measured anion gap and apply 2.5 times the difference between 4.0 g/dL and the actual serum albumin. https://jsbin.com/jigaqilocu A straightforward formula is: corrected anion gap = measured anion gap + 2.5 × (4.0 − serum albumin). This provides a useful calculation example for any medical calculator or manual check.
What is the standard correction used for albumin?
The standard correction is the 2.5 mEq/L per 1 g/dL albumin correction. It is commonly used because it gives a practical estimate for the albumin-adjusted anion gap and enhances diagnostic interpretation in patients with decreased albumin levels.
When is a adjusted anion gap be interpreted clinically?
Interpret the corrected anion gap when low albumin levels could be masking an acid-base problem, especially in suspected metabolic acidosis. It is most clinically useful when reviewing lab result interpretation in patients with unexplained illness, critical disease, or possible hidden acid accumulation.