What exactly is starvation ketoacidosis?
Starvation ketoacidosis is a form of metabolic acidosis that appears when the body does not receive enough carbohydrate intake or overall fuel and turns primarily to fat for fuel. This shift leads to ketosis, a state in which the liver produces ketone bodies to provide energy. When this process becomes more intense, acid production builds enough to affect acid-base balance and shift laboratory values.
The trigger is usually fasting, prolonged poor intake, or malnutrition. In these situations, the body experiences an energy deficit and a gradual drop in circulating glucose availability. As glucose availability falls, the body increases fat metabolism, which raises ketoacid production. This is different from everyday short-term ketosis because starvation states can produce a clinically meaningful acid-base disturbance.
Starvation ketoacidosis often occurs when nutritional deprivation is severe enough that the liver generates more acidic byproducts than the body can easily buffer. The main ketone-related acids are beta-hydroxybutyrate and acetoacetate. These compounds are part of normal ketone physiology, but in excessive amounts they contribute to metabolic derangement and a recognizable pattern of high anion gap metabolic acidosis.
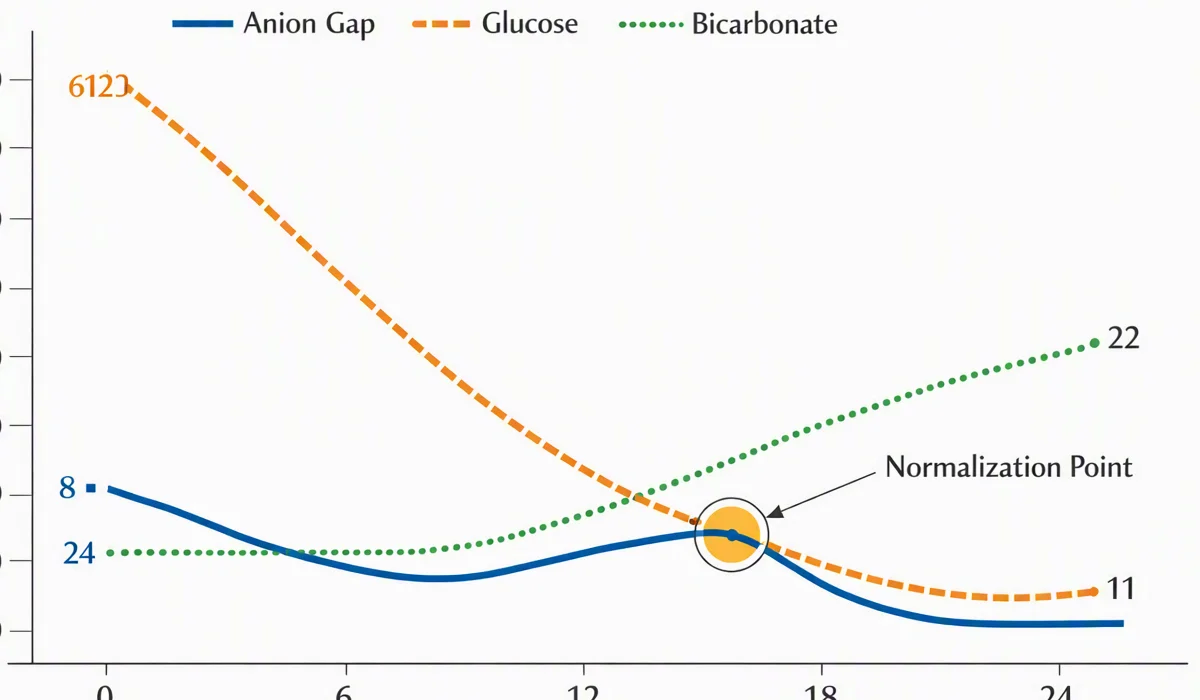
Understanding this process matters because not all ketosis is the same. In starvation ketoacidosis, the key issue is not simply the presence of ketones, but the combination of glucose depletion, acid generation, and the resulting change in laboratory interpretation. That is why the Anion Gap Calculator can be valuable as a quick tool for clinical interpretation of the lab pattern.
The Reason starvation ketoacidosis Elevates the Anion Gap
The anion gap goes up when acids accumulate in the blood and their charged components are not directly measured in a standard electrolyte screen. In starvation ketoacidosis, the major cause is the buildup of unmeasured anions produced from ketone bodies. As beta-hydroxybutyrate and acetoacetate increase, they deplete buffering capacity and leave behind negatively charged acid metabolites that elevate the gap.
This is the classic mechanism of a high-gap acidosis. The body responds to acid buildup by lowering bicarbonate, which is the primary buffer used during acidosis. As bicarbonate falls, the gap often increases because the lost buffer is functionally replaced by acidic anions that are not directly reflected in routine chemistry values.
The process is driven by ketone accumulation during prolonged fasting or nutritional deprivation. When insulin levels are relatively low and glucose intake is insufficient, the body shifts toward ketone production for fuel. This adaptive response becomes harmful when ketone generation outpaces utilization and elimination. The resulting organic acids alter acid-base balance and produce the elevated anion gap seen on labs.
Although both ketone bodies contribute, beta-hydroxybutyrate is often the dominant acid in more significant ketoacid states. Acetoacetate also increases the measured acid load, but the total burden depends on severity, duration, and physiologic stress. The important point is that the ketones function as organic acids, and their presence explains why starvation ketoacidosis is a true cause of anion gap calculation abnormalities rather than a benign lab curiosity.
Put simply: starvation creates an energy shortage, the body burns fat, fat metabolism yields ketones, and those ketones act as unmeasured acids. That chain of events is why the anion gap increases.
How to Work Out and Interpret the Anion Gap
An Anion Gap Calculator may help estimating whether the electrolyte profile supports a elevated-gap acidosis. The standard calculation relies on sodium, chloride, and bicarbonate:
Anion gap = sodium - (chloride + bicarbonate)
This formula is simple, but interpretation depends on the full clinical context. A elevated result suggests too many unmeasured anions, while a result within the normal range makes starvation ketoacidosis less likely or indicates an initial / weaker stage. Since laboratory reference ranges differ, the exact cutoff should be interpreted using the local laboratory values and the patient’s general condition.
In starvation ketoacidosis, the anion gap increases because bicarbonate is depleted neutralizing the acids formed by ketogenesis. The low bicarbonate often matches the extent of acidosis. At the same time, chloride may be relatively normal or may go up in mixed patterns depending on volume status and replacement fluids. Sodium is needed for the calculation and may also vary with dehydration, poor intake, or concurrent illness.
When using an Anion Gap Calculator, it can help to think in terms of clinical interpretation rather than a single number. A modestly elevated gap may still be significant if the patient has clear lack of intake, nausea and vomiting, poor oral intake, or visible ketosis. A markedly high value suggests a more severe metabolic acidosis or another additional cause of high anion gap metabolic acidosis.
For interpreting the result effectively, pair the gap with the rest of the laboratory results:
- Sodium: helps frame the overall calculation and assess hydration or dilutional effects. Chloride: helps determine whether the acidosis is accompanied by secondary or mixed changes. Bicarbonate: often falls as acid load increases and is a key marker of severity.
The calculation is only a single part of the puzzle. The aim is not only to identify an out-of-range result, but to link it to the typical pattern of ketotic state, acid-base imbalance, and the possible cause of the metabolic derangement.
Common Laboratory Findings in Starvation Ketoacidosis
Starvation ketoacidosis has a well-known laboratory picture, although the exact picture varies depending on the length of fasting, degree of malnutrition, and any underlying illness. The most helpful tests often include serum glucose, electrolytes, arterial blood gas, and serum ketones.
Serum glucose is often not elevated or low rather than markedly elevated. This remains a key clue separating starvation ketoacidosis from other forms of ketoacidosis. Because the underlying problem is insufficient intake rather than excess glucose, the glucose level may reflect depletion rather than hyperglycemia.
Electrolytes often show the biochemical signature of acid-base stress. The bicarbonate level is usually low, supporting the diagnosis of metabolic acidosis. Sodium and chloride may vary depending on fluid losses, vomiting, dehydration, or treatment before testing. Examining the complete set of serum electrolytes helps determine whether the picture is pure or mixed.
Serum ketones are typically positive, and if quantitative testing is available, elevated beta-hydroxybutyrate supports the diagnosis more strongly than a basic urine ketone screen alone. This is because urine ketone testing may underrepresent the burden of beta-hydroxybutyrate. In starvation states, beta-hydroxybutyrate can be disproportionately elevated and is a major driver of the acid load.
An arterial blood gas may show acidemia with a low bicarbonate and compensatory respiratory changes. A patient may develop compensatory hyperventilation as the body tries to lower carbon dioxide and offset the acid load. This respiratory response helps maintain pH, but it does not correct the underlying problem.
Findings often include:
- Low or normal serum glucose Low bicarbonate Positive serum ketones Elevated beta-hydroxybutyrate and acetoacetate Abnormal electrolytes Acid-base changes on arterial blood gas
These findings support the diagnosis, but they also help estimate severity. The more pronounced the acidosis and ketone burden, the more likely the anion gap is to be clearly elevated.
How It Varies Against Diabetic Ketoacidosis and Other Causes
Starvation ketoacidosis can appear similar to other forms of high anion gap metabolic acidosis, so distinguishing it from related conditions is important. Its closest mimic is diabetic ketoacidosis, but there are several key differences.
In diabetic ketoacidosis, the core issue is insulin deficiency, which drives severe ketone production and usually produces far higher glucose levels. Starvation ketoacidosis, by contrast, is driven by glucose depletion and inadequate intake. The patient may have typical or low glucose rather than marked hyperglycemia. That distinction shifts both the diagnostic thinking and treatment priorities.
Alcoholic ketoacidosis is another notable differential. It often occurs after poor intake combined with heavy alcohol use and may resemble starvation physiology. Like starvation ketoacidosis, it can produce ketone-related acids and an elevated anion gap. The broader context, however, differs, and alcohol use can add further metabolic complexity.
Lactic acidosis is another major cause of elevated gap metabolic acidosis. Instead of ketone bodies, lactate is the main unmeasured anion. Lactic acidosis may occur with tissue hypoperfusion, sepsis, or other forms of metabolic stress. If lactate is elevated, it can explain part or all of the gap, even if ketosis is present at the same time.
Renal failure can also raise the https://anion-gap-estimator556.huicopper.com/how-accurate-is-an-anion-gap-calculator gap because failing kidneys cannot clear acids effectively. In that setting, retained acids and other retained solutes contribute to the anion gap. Renal impairment can coexist with starvation or dehydration, which makes interpretation more challenging and reinforces the need for thorough diagnostic evaluation.
The key differences often come down to the pattern of labs and the clinical story:
- Diabetic ketoacidosis: usually marked hyperglycemia and insulin deficiency Starvation ketoacidosis: fasting, malnutrition, low or normal glucose, ketone-driven acidosis Alcoholic ketoacidosis: alcohol use plus poor intake, overlapping metabolic features Lactic acidosis: elevated lactate from hypoperfusion or stress Renal failure: impaired acid clearance and retained metabolic acids
Because these conditions can overlap, the best approach is to use the anion gap as a beginning point, not the final diagnosis. The gap identifies the presence of excess unmeasured anions, but only the rest of the clinical picture can determine the cause.
When a High Anion Gap Needs Immediate Evaluation
A elevated anion gap in every case merits care, but the level of concern depends on the severity, related symptoms, and the general acid-base disorder. Starvation ketoacidosis may be subtle in some cases, but it can still become serious if the patient is volume depleted, unable to eat, or has another illness adding to the metabolic disturbance.
Urgent evaluation is important when symptoms suggest increasing acidosis or systemic illness. These may include disorientation, pronounced weakness, persistent vomiting, rapid breathing, dehydration, or inability to sustain oral intake. A patient with clear acidemia on an arterial blood gas and an higher gap needs prompt clinical assessment rather than mere observation.
The concern is not only the ketones themselves, but the overall acid-base balance. If bicarbonate continues to drop, the acidosis can intensify. If the patient has concurrent infection, vomiting, renal impairment, or significant volume depletion, the metabolic picture can decline quickly.
Practical considerations during assessment include:
- How long the patient has had reduced intake or fasting Whether there is malnutrition or ongoing lack of adequate nutrition Evidence of ketosis or substantial ketone burden Whether serum glucose is below normal, normal, or increased Whether another cause of high anion gap metabolic acidosis may also be present
If the patient is symptomatic or the laboratory values show a significant metabolic derangement, the issue should be treated as beyond a simple electrolyte abnormality. The elevation in the anion gap is a marker of underlying acid production, and the cause for that acid load must be identified.
FAQs About Starvation Ketoacidosis and Anion Gap
Does starvation ketoacidosis always cause a raised anion gap?
Not always, but it frequently does. ketoacidosis from starvation typically increases the anion gap because ketone-related acids create unmeasured anions. In initial or subtle cases, the gap may be only slightly elevated or even appear almost normal if the acid load is limited or if other electrolyte changes are present. The overall clinical picture and anion gap interpretation matter as much as the number itself.
How elevated is the anion gap in ketoacidosis from starvation?
The level of elevation changes with the severity of ketosis, duration of fasting, and presence of other illnesses. Some cases show a modest rise, while more severe starvation ketoacidosis can produce clear high anion gap metabolic acidosis. The exact level is secondary than whether the result fits the rest of the picture, including bicarbonate, serum glucose, and ketone testing.

What lab tests help confirm ketoacidosis from starvation?
The most helpful tests include serum glucose, electrolytes, arterial blood gas, and serum ketones. Quantitative beta-hydroxybutyrate is especially helpful because it reflects the main ketone burden more accurately than some urine tests. These results, combined with the history of reduced intake or malnutrition, support the diagnosis.
In what way is fasting ketoacidosis different from DKA?
Diabetic ketoacidosis is driven by insulin deficiency and usually presents with much higher glucose levels. Fasting ketoacidosis is caused by glucose depletion from inadequate intake and often has typical or low serum glucose. Both can produce ketosis and elevated anion gap acidosis, but the trigger, lab pattern, and treatment approach differ.
Can the anion gap normalize to baseline after treatment?
Certainly. Once the underlying problem is addressed, ketone production drops, unmeasured anions go down, and the anion gap can come back toward normal. Management usually addresses the energy deficit, fluid balance, and electrolyte disturbances, which helps maintain acid-base balance. Repeat laboratory values are often used to verify improvement in metabolic acidosis and overall metabolic status.
Starvation ketoacidosis is a genuine acid-base disorder, not just a benign ketotic state. The key pattern is the rise in the anion gap from ketone-related organic acids, especially beta-hydroxybutyrate and acetoacetate, during periods of fasting or malnutrition. An Anion Gap Calculator helps you spot that pattern rapidly, but the most precise interpretation always comes from pairing the calculation with the clinical story, laboratory values, and careful medical assessment.