How the Anion Gap Is Measured
The anion gap is a computed value that assists medical professionals and patients see whether the body’s electrolyte levels are in balance and whether an acid-base balance problem may be present. It never detect a single substance directly. Instead, it estimates the difference between routinely measured positive and negative ions in the blood, which can point to clues about hidden acids or other hidden anions.
An anion gap calculator method is a practical diagnostic aid because it transforms routine serum chemistry results into a useful number for analysis. When the anion gap is beyond the expected range, it can point toward a metabolic acidosis, a different acid-base disorder, or another metabolic change that requires closer evaluation.
The calculation is usually based on a standard electrolyte test panel, especially the blood sodium level, chloride value, and blood bicarbonate level. These laboratory values provide a quick snapshot of the chemical environment in the bloodstream. Because the result is calculated, it should always be read in the clinical setting, not as a stand-alone diagnosis.
How the Anion Gap Calculator Works
A device that relies on blood chloride input typically requests the patient’s serum sodium, serum chloride, and serum bicarbonate. These three numbers are enough to calculate anion gap in the most common way. The tool then estimates the gap between major measured cations and anions, which helps reveal whether extra acids or other charged particles may be present.
In basic terms, the tool compares the sodium concentration against the combined effect of chloride and bicarbonate. This is why the accuracy of the chloride level matters so much. If chloride is unexpectedly high or low, the result can shift significantly, sometimes changing the impression from a normal anion gap pattern to a high anion gap or the reverse.
This type of anion gap calculator is particularly helpful when reviewing a serum chemistry report swiftly. It acts as a connector between raw laboratory values and bedside reasoning, giving a rapid estimate that can support broader clinical decision-making. Still, the calculator is only one part of the assessment; the numbers must be matched with symptoms, history, and other laboratory values.
Method for Calculating Anion Gap
The classic anion gap formula is:
Anion gap = serum sodium − (serum chloride + serum bicarbonate)
This formula takes serum sodium as the main measured cation and serum chloride plus serum bicarbonate as the primary measured anions. The remaining difference represents the balance of other ions not routinely measured in a basic panel.
Many clinicians use this value as a clue to the presence of unmeasured anions. For example, if the gap is elevated, it may indicate an accumulation of acids or acid-related substances. If the gap is lower than expected, it may reflect changes in albumin, chloride, or testing issues.
A calculator that uses blood chloride input is helpful because chloride is a key variable in the equation. Even small changes in serum chloride can affect the final result. That renders the tool valuable for reviewing an electrolyte panel, confirming a suspected acid-base issue, or helping explain why two similar serum chemistry reports may lead to different interpretations.
Standard Anion Gap Range and Meaning
The expected range for anion gap depends on the lab technique and the normal interval used by that laboratory. Different testing systems and measurement approaches may produce slightly different results, so there is no single cutoff that applies everywhere. That is why https://anion-gap-calculation.com/ the reported reference interval from the lab should always be checked first.
A normal value generally suggests that the major measured ions are in expected proportion and that no major accumulation of unmeasured acids is apparent from the calculation alone. However, a normal value does not automatically mean everything is okay. Some acid-base problems may still be present, especially if the pattern of sodium, chloride, and bicarbonate suggests another issue.
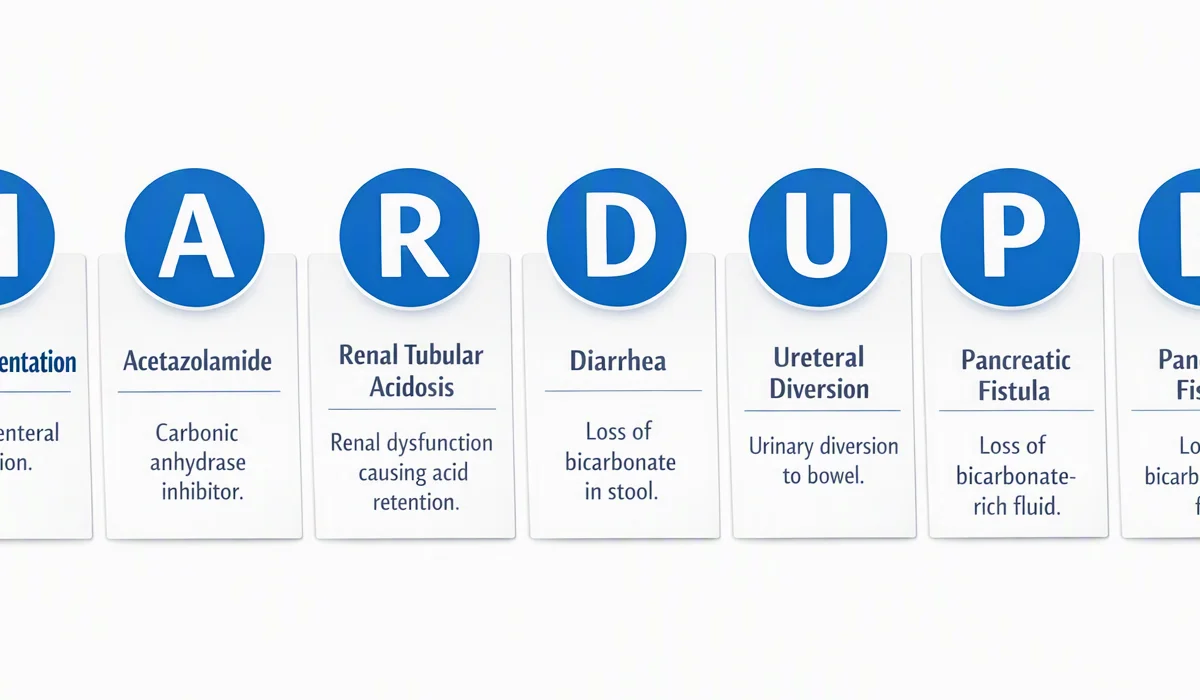
A high anion gap usually points toward additional acids in the blood, while a decreased anion gap is less common and may indicate changes in proteins, measurement issues, or unusual laboratory patterns. In all cases, the number should be interpreted alongside the patient’s symptoms, the electrolyte panel, and broader medical context.
Why Chloride Input Matters
Blood chloride is more than a secondary value; it is key to the result. Because chloride directly reduces the result in the anion gap formula, any increase or fall in serum chloride can meaningfully affect the outcome. This is why an anion gap calculator that specifically requires chloride input can provide clearer insight than a general explanation of the formula.
When chloride is elevated, a pattern called hyperchloremia may occur. This can lower the calculated gap and sometimes mask a simultaneous acid-base process. When chloride is decreased, or hypochloremia is present, the gap may go up or appear less straightforward to interpret. These chloride-related shifts are a reminder that the calculator reflects a relationship, not an standalone disease diagnosis.
For this reason, reviewing the chloride value alongside sodium and bicarbonate helps show whether the result reflects true physiology or just a change in one component of the electrolyte panel. In practice, the chloride level often provides the key that makes the interpretation more precise.
Typical Causes of an Elevated Anion Gap
A increased anion gap often indicates a buildup of acids that are not included in the standard electrolyte panel. One of the most common causes is lactate-related acidosis, which can occur when tissue oxygen delivery or utilization is impaired. Under these conditions, lactate increases and the anion gap rises as the body’s acid-base balance shifts.
Another important cause is acid buildup from ketones. This may occur when the body produces excess ketones, which act as unmeasured acids. The calculator can help identify this pattern, but the result must still be paired with blood glucose, symptoms, and other findings. A increasing gap in this context often reflects a substantial metabolic disturbance.
Impaired kidney function is also a classic cause of elevated gap values because the kidneys are less able to excrete acid and maintain normal electrolyte balance. As waste products accumulate, the anion gap may rise. In these scenarios, the calculator is best used as an first indicator rather than a final answer.
Typical Causes of a Reduced or Regular Anion Gap
A low anion gap is rarer than an elevated one, but it can be medically significant. A leading cause is hypoalbuminemia, since albumin is a negative-charged protein that contributes to the normal gap. When albumin falls, the calculated number may drop even if there is an existing condition present.
Lab error should also be kept in mind whenever the result seems out of line with the clinical picture. Because the anion gap depends on several lab values, small problems in sodium, chloride, or bicarbonate reporting can change the final value. That is why repeat testing or confirmation may be warranted when the number does not fit the patient’s condition.
Multiple myeloma can occasionally produce a low anion gap because abnormal proteins may disturb the balance of charged particles in the blood. This is another example of why the result should be read as part of a full workup rather than as a standalone screening test.
How to Understand Results in Clinical Context
Accurate interpretation begins with the raw numbers, but it does not end there. The best approach is to compare the result against the laboratory’s reference range, consider whether an acid-base disorder is present, and then review whether the pattern suggests a true metabolic acidosis or another imbalance.
Albumin correction is particularly important when serum albumin is low. Since albumin contributes to the normal measured gap, a patient with hypoalbuminemia may look to have a normal or low result even if hidden acids are present. A corrected anion gap can provide a more precise estimate of the underlying acid-base status in such cases.

The most effective approach is to combine the calculator result with the patient’s symptoms, history, and other laboratory values. That is the essence of clinical correlation. A number that appears only mildly abnormal may be significant in one setting and less important in another. Likewise, a “normal” value may not exclude an evolving condition if the rest of the acid-base picture suggests a problem.
Limitations of an Anion Gap Calculator
Even a carefully built anion gap calculator has limits. The result depends on the lab’s reference range, which can vary based on analyzer type and reporting method. Different institutions may also define the normal window differently, so the same numeric result may be interpreted differently across settings.
Lab variability is another major issue. Small changes in how sodium, chloride, or bicarbonate are measured can affect the final answer. Because the formula subtracts two values from sodium, tiny analytical differences can have a noticeable effect. This is especially relevant when the result is close to the upper or lower limit of normal.
Measurement error can also create misleading results. A sample problem, analyzer issue, or transcription mistake may make the gap appear abnormal when it is not. For that reason, the calculator should be viewed as a starting point for interpretation, not as definitive proof of disease. It is a helpful tool, but it cannot replace expert review of the full electrolyte panel and the patient’s clinical context.
Frequently Asked
How can you calculate an anion gap using blood chloride?
To work out the anion gap using blood chloride, use the standard anion gap formula: serum sodium minus the sum of serum chloride and serum bicarbonate. An anion gap calculator handles this for you once you enter the serum sodium, serum chloride, and serum bicarbonate values from the electrolyte panel. The result helps assess the balance of electrolytes and can aid in assessing an acid-base problem.
What does a high anion gap indicate?
A high anion gap usually indicates there are extra acids or other unmeasured anions in the blood. Common causes include lactic acidosis, ketoacidosis, and renal failure. It is often a clue to metabolic acidosis, but the result should always be interpreted with the complete patient picture, not in isolation.
Can a normal anion gap still indicate a problem?
Yes. A normal anion gap does not completely rule out disease. Some acid-base disorders may still be present even when the calculated value falls within the expected reference interval. For example, changes in chloride, bicarbonate, or albumin can affect interpretation. That is why the electrolyte panel and overall clinical context are important.
Why does albumin influence the anion gap?
Albumin is a major negatively charged protein in the blood, so it contributes to the normal anion gap. When albumin is low, the gap may appear lower than expected even if an acid-base disorder exists. This is why albumin correction and attention to serum albumin are important when reviewing results, especially in hypoalbuminemia.
When is it appropriate to repeat or confirm an anion gap result?
A result should be repeated or confirmed when it does not match the patient’s condition, when there is concern for lab error or measurement error, or when the value is borderline and affected by lab variability. Confirmation is also reasonable if the result is unexpectedly high, low, or inconsistent with other laboratory values. In those situations, reviewing the full electrolyte panel and repeating the test can improve confidence in the interpretation.