What the Anion Gap Assesses
The anion gap is a practical laboratory-derived estimate used in point-of-care and formal laboratory interpretation to help identify hidden shifts in serum electrolytes. It reflects the relationship between routinely measured cations and anions, most commonly serum sodium, serum chloride, and serum bicarbonate, with serum potassium sometimes included depending on the formula used. Clinically, it functions as a diagnostic marker for acid-base disorder evaluation, especially when metabolic acidosis is suspected.
The main value of the anion gap is that it reflects the burden of unmeasured anions in the blood chemistry. These may include lactate, ketones, sulfate, phosphate, and various toxins. A rise in the gap usually indicates a metabolic derangement that has added acid equivalents or reduced bicarbonate without a proportional increase in chloride. This is why the anion gap remains central to acid-base balance assessment and clinical assessment in acutely ill patients.
From a pathophysiology standpoint, the calculation is grounded in electroneutrality. Because standard chemistry panels do not measure every ion, the gap helps infer hidden contributors to systemic acidosis. In practice, the result can suggest whether the body is experiencing a chloride-driven process, a bicarbonate deficit, or accumulation of acids from toxic ingestion, hypoperfusion, or impaired renal excretion.
Most clinicians use the anion gap as part of a broader differential diagnosis. It is not a standalone diagnosis, but a structured way to interpret the pattern of electrolyte panel results in context. When combined with pH, bicarbonate, and the rest of the serum electrolytes, it can rapidly narrow the likely cause of acidosis and guide the next diagnostic step.
Using an Anion Gap Calculator
An Anion Gap Calculator simplifies the anion gap formula and reduces arithmetic errors during urgent clinical assessment. Most calculators ask for serum sodium, serum chloride, and serum bicarbonate; a few also request serum potassium. The calculator then displays the calculated gap and often indicates whether the result matches the expected reference range.
The standard formula without potassium is:
Anion gap = sodium − (chloride + bicarbonate)
When potassium is included, the equation becomes:
Anion gap = sodium + potassium − (chloride + bicarbonate)
To use it well, enter the exact lab values from the same sample whenever possible. Combining results from different draws can distort the result, especially in rapidly changing clinical states. The calculator is most useful when the chemistry panel, acid-base data, and bedside findings are interpreted together rather than in isolation.
During routine care, the calculator should be anion gap clinical significance paired with the broader picture of blood chemistry. For instance, a low bicarbonate with a high anion gap supports high-gap acidosis, but the source of the acid still requires further workup. If the gap is normal despite acidosis, the calculator may point toward a chloride-rich process or another type of acid-base disorder.
These practical tips improve accuracy:
- Use the same reporting units consistently. Confirm whether potassium is part of the local formula. Check for unexpected lab artifacts before overinterpreting a borderline value. Review the albumin level if the result seems discordant with the clinical picture.
The most useful Anion Gap Calculator output is not the number alone, but the interpretation pathway it triggers. A calculated gap that is unexpectedly high should prompt a search for lactic acidosis, ketoacidosis, renal failure, or toxic alcohols. A normal gap with persistent acidemia raises concern for gastrointestinal or renal bicarbonate loss, among other etiologies.
Normal vs Elevated Anion Gap
The normal anion gap is best interpreted as a window rather than a single fixed number because it changes by laboratory method, analyzer platform, and whether potassium is included. This is why the reported reference range from the local lab should guide interpretation. A value in the expected range does not automatically exclude disease; it simply indicates that the current acid-base pattern does not show a substantial burden of unmeasured ions.
An elevated gap is often the clue that shifts the differential toward high anion gap metabolic acidosis. In this setting, the accumulation of unmeasured acids decreases bicarbonate as chloride does not rise enough to fully offset the charge change. The resulting pattern is a marker of a clinically important acid-base disorder and often requires urgent evaluation for reversible causes.
By contrast, a normal anion gap in the presence of low bicarbonate typically suggests a hyperchloremic process. Here, chloride rises as bicarbonate falls, preserving electroneutrality and keeping the gap relatively stable. This pattern is frequently seen in diarrhea or renal tubular defects, but it can also be influenced by saline administration and other treatment-related shifts.
Understanding whether a patient has metabolic acidosis requires more than just a single chemistry result. A low bicarbonate with normal pH may reflect compensation, mixed disorders, or timing issues. Likewise, the anion gap may be elevated before pH becomes severely abnormal if respiratory compensation is intact. This is why interpretation should always include the full acid-base picture, not just the numeric gap.
Adjusted Anion Gap and Albumin Correction
Hypoalbuminemia is a key reason a measured gap can look misleadingly normal or only slightly high. Because albumin is a key unmeasured anion, reduced albumin lowers the baseline gap and may mask clinically meaningful acid accumulation. This is the basis for the corrected anion gap and broader anion gap correction strategy.
Interpretation with albumin correction helps avoid missing a high-gap process in critically ill patients. When albumin is low, the measured gap should be interpreted together with a correction factor rather than as a raw number alone. The goal is not to “normalize” the lab value cosmetically, but to uncover the true magnitude of the underlying electrolyte imbalance.
Many clinicians use an albumin-adjusted approach when the clinical suspicion for acidosis is high but the initial gap is mild. This matters in sepsis, liver disease, malnutrition, nephrotic states, and other conditions associated with hypoalbuminemia. Without correction, a dangerous acid load may be trivialized.
A practical approach is to check the albumin whenever the chemistry profile does not align with the bedside picture. If the albumin is low, reassessing the corrected anion gap can reclassify a borderline result into a clearly abnormal one. This improves diagnostic sensitivity for hidden metabolic acidosis and helps align the lab https://anion-gap-reader771.wpsuo.com/how-to-calculate-anion-gap interpretation with the patient’s physiology.
Albumin correction is especially important when the differential includes toxic or ischemic etiologies. In those situations, a falsely reassuring value can slow intervention. Using correction routinely in the appropriate context lowers the chance of missing a significant metabolic derangement.
Frequent Causes of elevated anion gap metabolic acidosis
High anion gap metabolic acidosis indicates the build-up of acid precursors or acid precursors that contribute to unmeasured ions. The leading causes in clinical practice include lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. Each has separate mechanisms, but they follow the same laboratory pattern: a drop in bicarbonate with a larger gap.
Lactic acidosis arises when tissue reduced blood flow, low oxygen levels, mitochondrial dysfunction, or severe metabolic stress drives lactate production faster than removal. It is common in shock conditions, sepsis, seizures, and profound anemia. The anion gap may rise abruptly, making it an prompt indicator of occult hypoperfusion and worsening systemic acidosis.
Ketoacidosis occurs when ketone production outpaces utilization and elimination. Diabetic ketoacidosis is the classic example, but starvation and alcohol-related states can also produce a notable gap. The extent of acidemia varies, and the final pattern depends on insulin status, volume depletion, and compensatory respiratory response.
Renal failure contributes by reducing acid excretion and allowing retention of sulfate, phosphate, and other acidic solutes. In advanced kidney dysfunction, the gap may rise progressively or considerably depending on the degree of retained acids and concurrent therapies. A worsening gap in renal failure should prompt review of the trajectory and any superimposed lactic or ketoacidotic process.
Toxic alcohols remain a critical diagnosis not to miss. Ethylene glycol, methanol, and related substances can cause pronounced high-gap acidosis through metabolite accumulation. The anion gap may be elevated before the osmolar gap closes, so repeat testing and careful history are essential. In any suspected toxic ingestion, the gap is a helpful clue but never definitive on its own.
Additional factors can involve salicylates, rhabdomyolysis, and certain inborn errors, but the major practical framework remains the same: determine the acid source, assess severity, and judge whether urgent antidotal or supportive treatment is needed. The calculator is best viewed as an entry point into a structured diagnostic workup.
Typical Causes of Normal Gap Metabolic Acidosis
A normal anion gap metabolic acidosis is usually a chloride-related process in which bicarbonate is removed or exchanged in a way that keeps the measured gap. The two most common clinical causes are diarrhea and RTA. In these settings, the lab pattern often points toward chloride-associated acidosis.
Diarrhea causes direct bicarbonate depletion from the gastrointestinal tract. As bicarbonate falls, chloride rises to support electroneutrality, resulting in a relatively normal gap. The history is often decisive, but the chemistry panel can verify the physiology when symptoms are incomplete or communication is limited.
Tubular kidney acidosis reflects reduced renal acid handling or bicarbonate reclamation. Different subtypes affect distal acid secretion or proximal bicarbonate reabsorption, but the final blood chemistry can be similar: low bicarbonate, relatively preserved anion gap, and often hyperchloremia. Recognition matters because management may differ by subtype and chronicity.
Hyperchloremic acidosis may also appear after substantial chloride-rich fluid administration or in settings where bicarbonate is replaced by chloride at the kidney or gut level. This is an critical reminder that the gap is a recognition pattern tool, not a diagnosis in itself. Correlation with iatrogenic exposures, kidney function, and GI losses is essential.
In all normal-gap states, the question is not simply “why is the gap normal?” but “what mechanism is replacing bicarbonate with chloride or preventing acid excretion?” That physiologic question guides the next step in workup and management.
Clinical Interpretation and Further Steps
Assessing the anion gap in practice starts with the acid-base data and then broadens into the full clinical picture. An arterial blood gas is often the best next study when the chemistry panel suggests important abnormality. The blood gas helps confirm the pH, evaluate respiratory compensation, and reveal mixed disorders that are not obvious from chemistry alone.
The delta gap is important when the measured gap is elevated. It weighs the rise in the anion gap with the fall in bicarbonate to determine whether a second metabolic process is present. A disproportionately large gap rise relative to bicarbonate decline may suggest concurrent metabolic alkalosis; a smaller-than-expected change may indicate a mixed high-gap and normal-gap acidosis. This step improves diagnosis beyond the initial screening value.
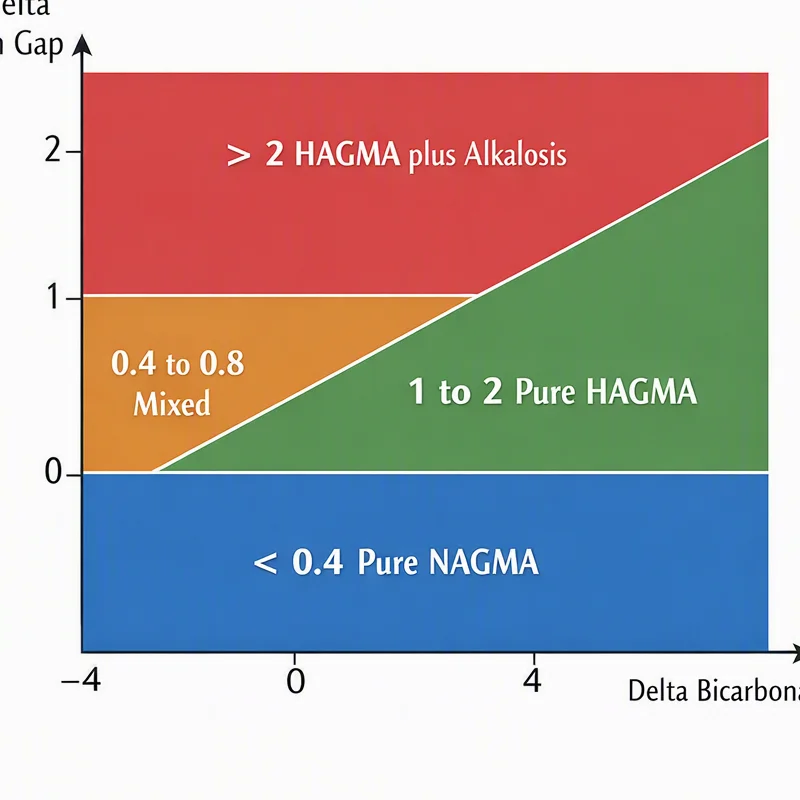
Base status also matters. A significant base deficit supports clinically relevant acid burden and helps track severity over time. In shock, sepsis, or toxin exposure, it may provide a useful serial indicator alongside serial lactate, renal function, and repeated electrolyte measurements.
A practical workflow is:
- Verify the chemistry values and calculate the gap. Examine albumin and apply correction if needed. Obtain the arterial blood gas for pH and compensation. Interpret the delta gap when the gap is elevated. Look for the underlying cause based on the pattern and clinical context.
In a patient with high-gap acidosis, emphasize rapid identification of lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. In a normal-gap acidosis, consider diarrhea, renal tubular acidosis, and other sources of bicarbonate loss. If the picture is mixed or uncertain, reassess the labs, review prior values, and re-evaluate the trajectory rather than anchoring to one result.
Constraints of Anion Gap Calculation
Despite its utility, the anion gap has significant limitations. Laboratory variation can change the expected range between institutions and analyzers, so a number that is “normal” in one setting may be mildly abnormal in another. This is one reason local reference intervals should always be used for interpretation.
Analytical error is another issue. Minor inaccuracies in sodium, chloride, or bicarbonate can materially change the calculated result, especially when the gap is borderline. Pre-analytical problems, sample handling, and analyzer-specific bias all affect the output. If the value does not fit the clinical picture, repeat testing is often appropriate before making major decisions.
Another major limitation is the influence of unmeasured cations. Lithium, marked hypermagnesemia, and other cation excess states can lower the gap and obscure underlying acidosis. Likewise, shifts in calcium or paraproteins may alter interpretation in select cases. The calculator cannot fully account for these possibilities without broader clinical data.
Most critical of all, the anion gap must always be interpreted in clinical context. The same value can mean different things depending on kidney function, albumin, ventilation, perfusion, medications, and timing. The calculator supports clinical judgment, but it does not replace judgment, trend review, or diagnosis by cause.
If used correctly, the tool is a powerful aid to interpretation of laboratory results. When used alone, it can mislead. The best practice is to integrate the gap with symptoms, serial chemistry, gas exchange, and the broader physiologic picture.
Common Questions
What is the formula for calculating the anion gap?
The most commonly used anion gap equation is sodium minus the sum of chloride and bicarbonate. Certain clinicians include potassium as well, depending on local convention and the calculator used. The key is to apply the same method consistently and interpret the result against the relevant laboratory reference range.
What is the reason for albumin correction important while interpreting the anion gap?
Albumin acts as a major nonmeasured anion, so hypoalbuminemia decreases the apparent gap and can obscure a true acid burden. A corrected anion gap or albumin-adjusted interpretation boosts detection of hidden high-gap states and lowers the risk of underestimating metabolic acidosis.
What can a high anion gap indicate from a clinical standpoint?
A high gap usually suggests accumulation of unmeasured anions from conditions such as lactic acidosis, ketoacidosis, renal failure, or toxic alcohols. It is a pointer to high anion gap metabolic acidosis and should trigger a focused search for the underlying cause.
Is it possible for the anion gap to be normal in metabolic acidosis?
Yes. A normal anion gap can occur in metabolic acidosis when bicarbonate is lost and replaced by chloride, producing hyperchloremic acidosis. Common causes include diarrhea and renal tubular acidosis, both of which can lower bicarbonate without widening the gap.
What are main limitations of using an anion gap calculator?
The main limitations include lab variation, measurement error, the influence of unmeasured cations, and dependence on clinical context. The calculator is helpful for screening and pattern recognition, but it cannot replace a full acid-base evaluation, including the arterial blood gas, albumin review, and cause-specific differential diagnosis.