What Anion Gap Means and Why It Is Important
The anion gap is a valuable lab-calculated value used to detect the cause of metabolic acidosis and additional abnormalities in electrolytes. In the emergency department, it serves as a rapid screening tool for acid-base balance problems and helps clinicians refine a broad differential into a focused diagnostic algorithm.

An anion gap calculator is helpful because the underlying concept is simple, but the interpretation is not. A patient may present with an apparently mild metabolic derangement, yet the pattern of serum electrolytes can reveal serious illness such as lactic acidosis, ketoacidosis, toxic ingestion, or renal failure. The gap represents the difference between measured cations and measured anions, which reflects unmeasured anions in the blood.
For emergency medicine, the anion gap is not just a number. It is a piece of clinical decision support that assists in determining whether the patient likely has high anion gap metabolic acidosis, normal anion gap metabolic acidosis, or another acid-base disorder instead. It also guides whether to obtain additional studies such as a venous blood gas, lactate, ketones, toxicology testing, or an osmolar gap.
How to Determine the Anion Gap
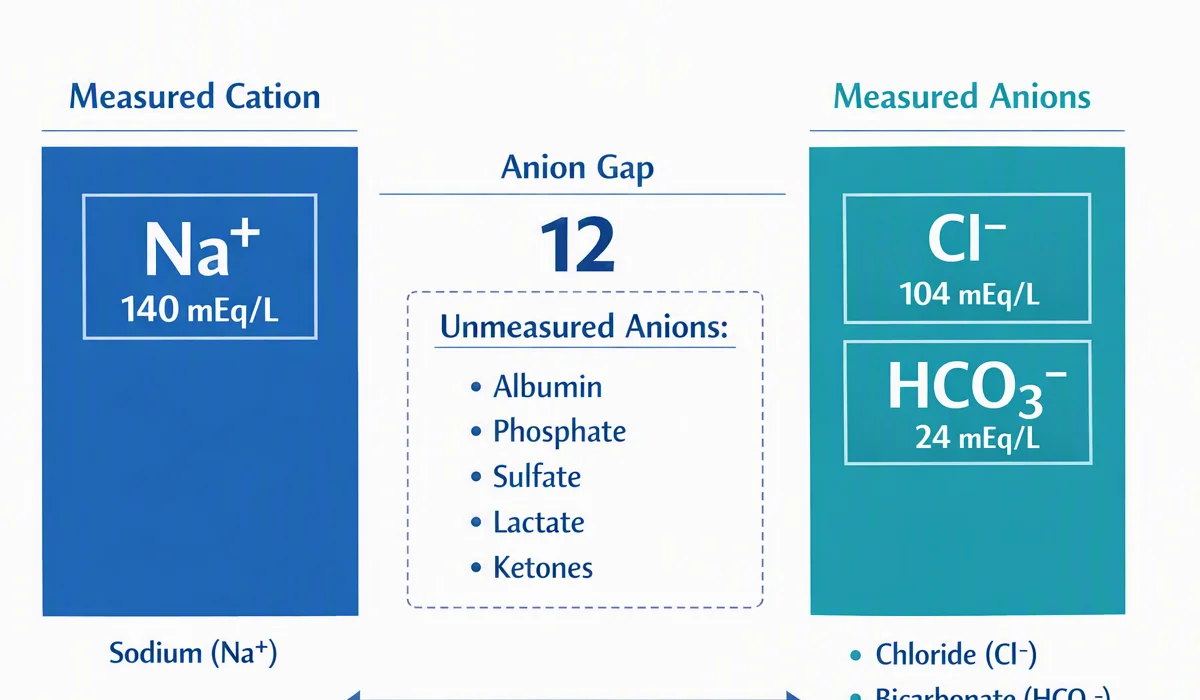
The usual anion gap formula is based on the main measured electrolytes: sodium, chloride, and bicarbonate. A typical expression is:
Anion gap = Sodium − (Chloride + Bicarbonate)
A few laboratories and references may also include potassium, but for emergency care, the sodium-based formula is the most common because it is straightforward, quick, and widely available on the basic metabolic panel. The result reflects the amount of anion deficit from unmeasured ions.
For example: if sodium is 140, chloride is 104, and bicarbonate is 20, the calculation is 140 − (104 + 20) = 16. That value may be within normal limits or slightly high depending on the lab reference range and the patient’s clinical context.
An anion gap calculator automates this diagnostic calculation, limiting manual errors during time-sensitive critical care evaluation. It also helps clinicians easily assess sequential results from an electrolyte panel when monitoring a patient’s response to treatment.
Using the Anion Gap Calculator in acute care
In the ER, the calculator is especially useful when a patient has unexplained tachypnea, altered mental status, hypotension, vomiting, dehydration, or concern for toxicity. It is typically used alongside the BMP, point-of-care testing, and sometimes blood gas analysis.
Rapid testing can provide immediate sodium, chloride, and bicarbonate values that allow clinicians to identify metabolic abnormalities early. This matters when the patient may be deteriorating and decisions about fluids, insulin, bicarbonate, antidotes, or dialysis need to be made quickly.
Practical use in the ER often follows this sequence:
- Assess the lab results and calculate the anion gap. Determine whether the patient has metabolic acidosis on a venous blood gas or arterial sample. Evaluate whether the pattern suggests increased anion gap metabolic acidosis or hyperchloremic metabolic acidosis. Pursue confirmatory tests such as lactate, beta-hydroxybutyrate, ketones, renal function, or toxicology studies.
The value of the calculator is not in isolation, but in the way it strengthens result interpretation and supports early recognition of dangerous disease. In a fast-paced ED workflow, it is one of the most efficient ways to screen for major acid-base pathology.
Typical, Increased, and Reduced Anion Gap Results
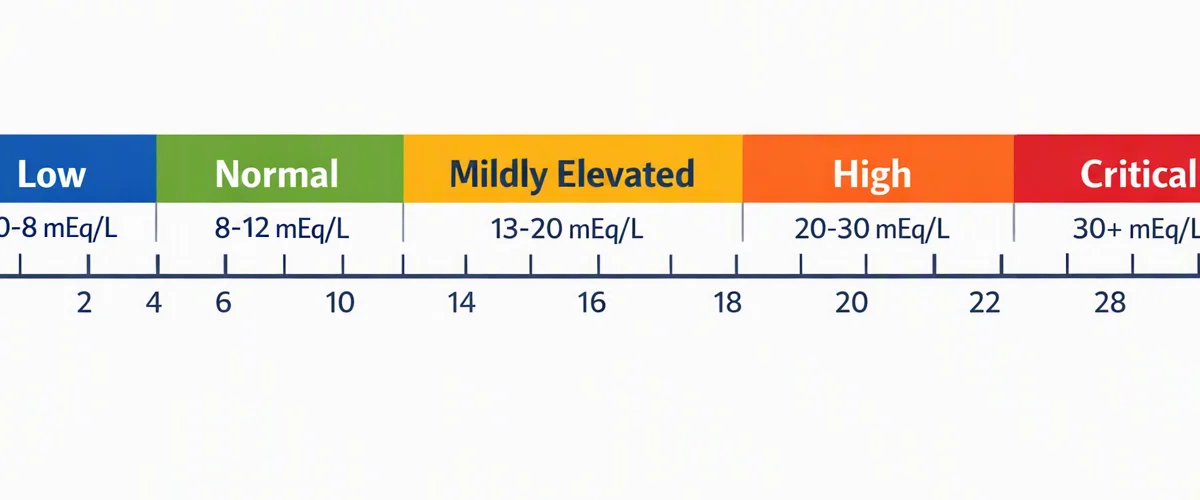
A normal anion gap usually indicates that any acidosis present is caused by loss of bicarbonate or chloride retention rather than by build-up of unmeasured acids. However, “normal” depends on the lab technique and comparison range, so clinicians should always interpret the value using site standards.
Increased anion gap metabolic acidosis suggests an excess of unmeasured acids in the blood. This is the result that often triggers urgent evaluation for lactate-related acidosis, ketoacidosis, toxic alcohols, and renal failure. It is a key signal in medical evaluation when a patient appears ill or has worrying vital signs.
A low anion gap is less common and can be ignored. It may occur with severe albumin deficiency, laboratory artifact, or occasionally other less common clinical conditions. Although a low value is not usually the main immediate problem, it should prompt reconsideration of the test result and the broader acid-base imbalance.
For practical interpretation, the anion gap should be seen as a pattern-recognition tool rather than a stand-alone diagnosis. The presence of a normal or abnormal gap helps shape the next step in the diagnostic algorithm, not replace it.
Common Causes of a High Anion Gap
Various conditions can result in high anion gap metabolic acidosis, and the emergency provider should prioritize rapid exclusion of serious causes. The key and most common include lactic acidosis, ketoacidosis, and exposure to toxic alcohols.
Lactic acidosis often arises in shock, hypoperfusion, seizures, severe infection, or tissue ischemia. In the ED, this is a top concern in patients with possible sepsis, hypotension, or respiratory compromise. The anion gap may increase as lactate accumulates and uses up bicarbonate during buffering.
Ketoacidosis occurs when ketone bodies accumulate as organic acids. Diabetic ketoacidosis is the typical emergency presentation, but starvation or alcoholic ketosis can also play a role. The bicarbonate level often falls markedly, and the anion gap rises because ketones are unmeasured anions.
Toxic alcohols are another major cause of a high gap. Ethylene glycol and methanol are especially important because they can lead to serious organ injury and may initially present with nonspecific symptoms. In these cases, the anion gap may become elevated later in the course, so timing matters. An elevated gap with suspicion of ingestion should prompt consideration of an osmolar gap and immediate toxicity screening.
Other causes may exist, but these three are the emergency priorities because they are urgent and potentially reversible with early intervention.
Frequent Causes of Normal-Gap Acidosis
Normal anion gap acidosis is often linked to reduced bicarbonate or limited acid excretion. The hallmark lab pattern often includes a fall in bicarbonate with a compensatory increase in chloride, creating hyperchloremic acidosis.
Diarrhea is a frequent cause. Gastrointestinal bicarbonate loss can reduce serum bicarbonate while chloride increases to preserve electrical neutrality. This is a classic example of how the shift in chloride helps maintain balance on laboratory reports while the patient remains metabolically acidotic.
RTA is another important cause. In this condition, the kidneys fail to acidify the urine sufficiently or retain bicarbonate, leading to ongoing acidosis despite a normal anion gap. It is important to recognize this because it may suggest an underlying or chronic kidney issue rather than a brief illness.
Normal-gap acidosis can also occur after substantial saline infusion, though the major emergency causes to keep in mind remain diarrhea, tubular acidosis, and bicarbonate loss through the kidneys. Reviewing fluids, medicines, and recent illness helps differentiate these causes.
In What Way Does the protein albumin Affect the anion gap
the protein albumin serves as the primary unmeasured anion in plasma, so a low albumin level can artificially decrease the anion gap. This matters because a patient may have a clinically significant acidosis that appears not as severe on the initial calculation.
For this reason clinicians often use a adjusted anion gap when hypoalbuminemia is present. A typical approach is to adjust the measured gap upward when albumin is below normal, which helps uncover hidden excess acids. The exact correction method may vary by institution, but the principle is the same: low albumin can conceal a dangerous elevation.
This correction is especially relevant in critical care and in patients with liver disease, malnutrition, inflammation, or chronic illness, where low albumin is frequent. Without correction, the anion gap may downplay the true degree of metabolic derangement.
In practice, a corrected calculation strengthens test interpretation and can uncover a masked high gap when the raw result appears misleadingly normal. For that reason the anion gap calculator is most useful when used together with albumin data rather than used alone.
Sequential Interpretation in the ED
Interpreting the anion gap in the emergency department should take a clear approach. The goal is to detect the underlying acid-base disorder quickly and see whether immediate treatment is needed.
First: Confirm the chemistry values. Review sodium, chloride, and bicarbonate from the basic metabolic panel or point-of-care source. Make sure the result is plausible and not obviously affected by laboratory error.
Step 2 — Determine whether the patient has metabolic acidosis on a venous blood gas or other blood gas measurement. A low bicarbonate alone is not enough; pH and respiratory compensation help outline the full picture.
Then: Label the gap as normal, elevated, or low. If elevated, prioritize lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. If normal, focus on bicarbonate loss or chloride excess.
Step 4: If the presentation suggests ingestion, check the osmolar gap. An elevated osmolar gap with metabolic acidosis increases concern for toxic alcohol exposure, especially when clinical findings are unclear.
Step 5 — Weave together all findings with the story. The same lab result means something different in a stable patient with mild diarrhea than in a hypotensive patient with altered mentation and respiratory distress.
This systematic method is essentially a bedside diagnostic algorithm that integrates the calculator with patient status, blood gas data, and additional labs. It is a practical example of metabolic evaluation in real-time care.
Constraints and Caveats of the Calculator
Like any diagnostic calculation, the anion gap calculator has limitations. Small differences in lab methods can create measurement variation, so the exact normal range can differ between institutions and analyzers.
Laboratory error can also mislead interpretation. Hemolysis, specimen handling issues, or inconsistent repeat values may produce a result that does not fit the clinical picture. When the number and the patient do not match, repeat testing and correlation with other data are essential.
The calculator does not replace the clinical context. A small increase may still be very important in a poisoned, unstable patient, while a higher result may be chronic or somewhat compensated in a patient with known kidney disease. The anion gap should therefore be interpreted as part of the overall clinical picture rather than as a single trigger.
Other pitfalls include failing to account for albumin, treating every elevated gap as a single-cause problem, or not looking for a mixed disorder. The most accurate interpretation usually comes from combining the anion gap with blood gas findings, renal function, ketones, lactate, and toxin screening when indicated.
When to Escalate Evaluation or Treatment
Escalate without delay when the anion gap suggests a serious condition such as sepsis, renal failure, or poisoning. These are more than laboratory abnormalities; they are time-sensitive emergencies that can worsen quickly without treatment.
In suspected sepsis, an elevated gap plus elevated lactate or hemodynamic instability should lead to immediate resuscitation, cultures, antimicrobial therapy, and source evaluation. In renal failure, worsening acidosis may require nephrology input, close electrolyte monitoring, and possible renal replacement https://anion-gap-calculation.com/causes/high.html therapy depending on the overall picture.
For suspected poisoning, especially with toxic alcohols, ethylene glycol, or methanol, do not wait for confirmatory results if the clinical suspicion is high. The combination of acidosis, elevated gap, and possible osmolar gap can justify urgent antidotal therapy and consultation with toxicology.
Escalation is likewise appropriate when the patient has worsening mental status, respiratory fatigue, shock, or rapidly changing laboratory values. The calculator should guide the next action, not hold it up.
Frequently Asked Questions
What is the anion gap calculator used for?
The anion gap calculator is used to quickly estimate the anion gap from serum sodium, chloride, and bicarbonate values. In emergency medicine, it helps clinicians recognize metabolic acidosis, classify acid-base disorders, and decide whether further evaluation for lactic acidosis, ketoacidosis, toxic alcohols, or renal failure is needed.
What is the reference range for the anion gap?
The usual range depends on the laboratory method and reference standard used by that laboratory. Because assay methods vary, clinicians should interpret the value using the local lab’s range rather than relying on a one universal threshold. In practice, the result is best understood in combination with the patient’s symptoms, bicarbonate level, and overall acid base status.
How do you calculate a corrected anion gap for albumin?
To estimate a corrected anion gap, clinicians modify the measured result upward when albumin is low because hypoalbuminemia can hide a true elevation. The exact correction formula can vary, but the goal is the same: account for the effect of low albumin on the gap so that significant metabolic acidosis is not missed. This is especially useful in patients with ongoing disease, liver disease, or critical illness.
What leads to a high anion gap in emergency medicine?
The most important causes of high anion gap metabolic acidosis in emergency medicine include lactic acidosis, ketoacidosis, and toxic alcohols such as ethylene glycol and methanol. Other important causes include sepsis and renal failure. The anion gap should be interpreted with blood gas results, lactate, ketones, renal studies, and the patient’s overall status.
When should an osmolar gap be checked with anion gap results?
An osmolar gap should be checked when there is concern for ingestion, especially if the patient has unexplained acidosis, altered mental status, or a history that suggests possible exposure to toxic alcohols. It is particularly useful when evaluating possible ethylene glycol or methanol poisoning. In the ED, the osmolar gap adds another layer of poisoning screening to the broader metabolic evaluation.