What the Anion Gap Shows in Blood Chemistry
The anion gap is a calculated value used in laboratory chemistry to aid in interpreting electrolytes and assess acid-base balance. It shows the difference between major measured cations and anions in the blood, mainly sodium and chloride, with bicarbonate included in the comparison. Because routine testing does not directly measure every ion in circulation, the anion gap helps reveal the presence of unmeasured anions and other shifts in the body’s buffering system.
In practical lab interpretation, the anion gap is a clinical tool rather than a definitive diagnosis. It is often used to evaluate a possible acid-base disorder, especially when a clinician is trying to determine whether a metabolic disturbance is present. A normal result suggests the measured ions are balanced in a way that fits the expected electroneutrality of plasma, while an abnormal result can point to an electrolyte imbalance or hidden acids that are not obvious from the basic panel alone.
How an Anion Gap Calculator Functions
An Anion Gap Calculator employs a basic formula to the values input from a lab report. Many calculators use serum sodium, serum chloride, and serum bicarbonate, and some also include potassium. The calculator then returns a calculated value that aids lab interpretation by indicating whether the measured ions suggest an acid-base issue.
In the most common approach, the calculator subtracts chloride and bicarbonate from sodium. If potassium is included, the formula may change slightly, but the basic idea is the same: contrast major measured ions against the expected balance. Because the result is a calculated value, its meaning depends on the surrounding serum electrolytes, the patient’s clinical state, and the interpretive context of the rest of the report.
This makes the calculator useful as a diagnostic marker in clinical chemistry. It does not take the place of direct testing or clinical judgment, but it helps determine whether the lab result may reflect an anion deficit, anion excess, or a broader metabolic disturbance.
Conventional Anion Gap Formula and Reference Range
The classic anion gap formula is often written as:
Anion gap = sodium − (chloride + bicarbonate)
A few laboratories also use a potassium-inclusive variation, but the sodium-based version is the most widely recognized in routine lab science. The result is then compared with a normal range or reference interval supplied by the laboratory performing the test.
The exact reference interval can change because different instruments, reagents, and reporting methods may produce slightly different values. That is why the result should always be interpreted against the lab’s own serum chemistry panel reference interval rather than relying on a universal cutoff. A result that appears abnormal in one lab may remain within another lab’s normal range.
From a lab science perspective, the anion gap is a helpful summary of the relationship between measured ions and unmeasured ions. It is not a direct https://anion-gap-reference105.inkharbory.com/posts/anion-gap-calculator-with-detailed-results measurement of acid or base, but rather a calculated clue that may indicate the need for further testing, including a blood gas or additional chemistry studies.
Revised Anion Gap for Albumin
Albumin is a major unmeasured anion in blood, so low albumin can reduce the apparent anion gap. This is why many clinicians and laboratorians use a corrected anion gap when the patient has hypoalbuminemia. Without albumin correction, the result may underestimate the presence of an acid load.
The corrected value is especially important in patients with illness, inflammation, malnutrition, liver disease, or fluid shifts that reduce albumin concentration. In these cases, the unadjusted anion gap may look normal even though a true acid-base problem exists. An albumin-adjusted interpretation may uncover the hidden contribution of the reduced protein buffer.
For lab interpretation, albumin correction improves the usefulness of the anion gap as a diagnostic aid. It improves the connection between the numeric result and the patient’s real metabolic state. In other words, the corrected anion gap provides better interpretive context when low albumin could otherwise mask clinically important changes.
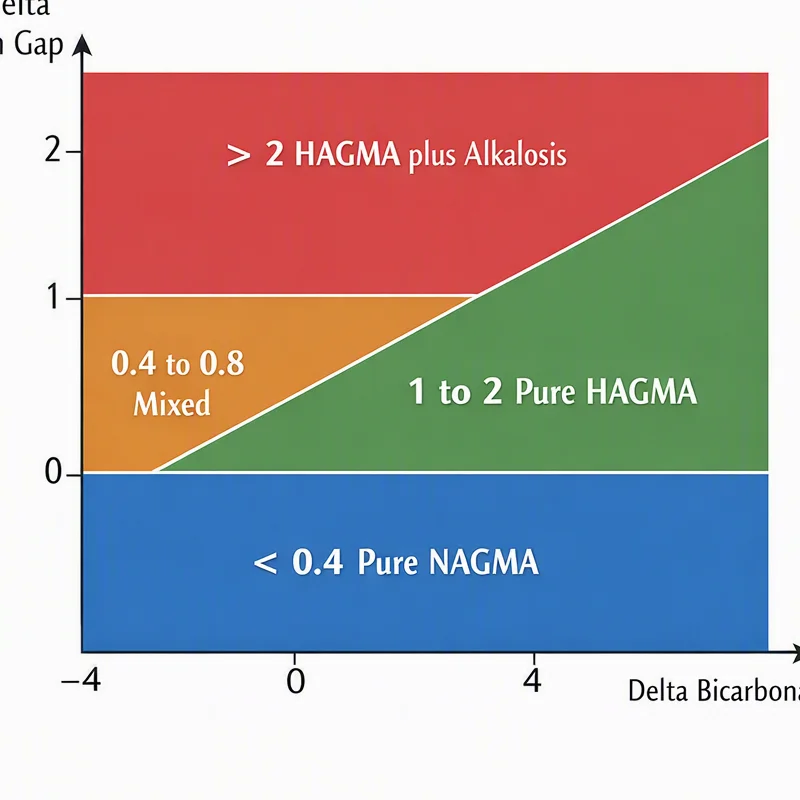
High Anion Gap vs Reduced Anion Gap
A elevated anion gap usually suggests an increased amount of acid or buildup of unmeasured anions. This pattern is often linked to metabolic acidosis, where bicarbonate is depleted as the body buffers acid. A high value is a sign that the balance between measured ions and unseen ions has shifted in a meaningful way.
A reduced anion gap is less common and can be the result of lab or physiologic factors. It may indicate low albumin, abnormal proteins, or analytical issues, among other possibilities. Because the low result can be subtle, it is important to verify the numbers and review the broader electrolyte panel before drawing conclusions.
Both patterns require close lab interpretation. A high result often points toward added acids, while a low result may indicate reduced negative charge from albumin or analysis-related issues. Either way, the value should be read as part of the overall clinical picture rather than as an isolated finding.
Frequent Causes of an Abnormal Anion Gap
Several conditions can move the anion gap away from the expected value. One of the most important is lactic acidosis, in which lactate accumulates as tissues generate energy under stress or inadequate oxygen availability. Another common cause is ketoacidosis, where ketone production goes up and adds additional acids to the blood.
Renal failure can also result in an abnormal result because the kidneys are less able to clear acid and support normal electrolyte handling. As retained acids and related compounds increase, the gap may rise. In addition, toxins can trigger a high anion gap by adding unusual acids or by interfering with metabolism in ways that boost acid load.
All of these causes fit the same overall pattern: the body accumulates unmeasured ions or loses buffering capacity, and the calculated value goes up. In the lab, this makes the anion gap a helpful clue in distinguishing one metabolic disturbance from another.
How to Use the Calculator in Steps
Working with Anion Gap Calculator is simple when the lab values are available. Start by identifying the input values from the report, then enter the serum sodium, serum chloride, and serum bicarbonate. If supported, include potassium as well.
After entering the numbers, review the calculated result and compare it with the lab’s reference range. When the tool provides a corrected output, enter the albumin value so the tool can estimate the corrected anion gap. This is especially important when hypoalbuminemia is present.
After the calculation is finished, interpret the result in context. A single number does not diagnose an acid-base disorder by itself. Instead, use it as part of a wider assessment that includes the electrolyte panel, the serum chemistry panel, and any other available clinical information.
Clinical & Lab Assessment Tips
Good clinical interpretation begins with reviewing whether the result aligns with the larger picture of acid-base status. When the anion gap is increased, watch for signs of metabolic acidosis and consider whether the patient may have lactic acidosis, ketoacidosis, renal failure, or toxin exposure. When the value is decreased, check albumin, total protein, and the possibility of analytical variation.
A blood gas can be very helpful because it offers direct information about pH, carbon dioxide, and bicarbonate handling. When paired with the anion gap, it gives a clearer view of whether there is a true acid-base disorder and whether compensation is occurring. This combination is often more useful than any one lab result alone.
It is also important to account for analytical pitfalls. Small shifts in measured ions can change the calculated value, and differences between instruments can affect the reported reference interval. For this reason, the anion gap should be interpreted alongside the electrolyte panel, the serum chemistry panel, and the patient’s clinical status. That approach supports diagnostic clarity and reduces the risk of overcalling or missing an abnormality.
Anion Gap Calculator FAQs
What is an anion gap calculator used for?
An Anion Gap Calculator is used to estimate the anion gap from lab values and help evaluate electrolyte balance, acid-base balance, and possible metabolic acidosis. It is a practical aid that supports lab interpretation by highlighting changes in measured ions and unmeasured ions.
What is the normal anion gap range?
The normal range depends on the laboratory and its reference interval. Different methods and instruments can produce different expected values, so the result should always be compared with the range reported on the specific serum chemistry panel.
Why does low albumin affect the anion gap?
Albumin is a major unmeasured anion, so hypoalbuminemia can lower the measured anion gap. That is why an albumin correction or corrected anion gap is often needed to avoid missing an underlying acid-base disorder.
What can cause a high anion gap?
A high anion gap is frequently seen with lactic acidosis, ketoacidosis, renal failure, and certain toxins. These issues increase unmeasured anions or reduce the body’s ability to maintain acid-base balance.
Should the anion gap be read with other lab results?
Yes. The anion gap should always be interpreted with the electrolyte panel, blood gas, albumin, and the rest of the clinical picture. This broader approach improves clinical interpretation and helps distinguish a true metabolic acidosis from other lab patterns.